Most people think implants create shape — they don't. At RG Aesthetic Plastic Surgery, breast augmentation is a structural planning problem: your anatomy, your tissue, your chest wall, and your goals all decide the plan. The implant is one variable.

Patients arrive focused on implant size. But whether a result looks natural or artificial, holds its shape or bottoms out, suits your body or fights it — those outcomes are decided elsewhere.
Submuscular, dual-plane, or subglandular positioning each creates a different relationship between implant and tissue — affecting how natural the result looks and how well it holds.
Width, projection, and height must match your chest wall and tissue coverage — not just the size that appeals in photographs.
Silicone vs. saline, smooth vs. textured, round vs. shaped — each has appropriate applications that depend on your anatomy.
Your existing tissue determines how much of the implant edge will be visible and palpable — and how much internal support is needed.
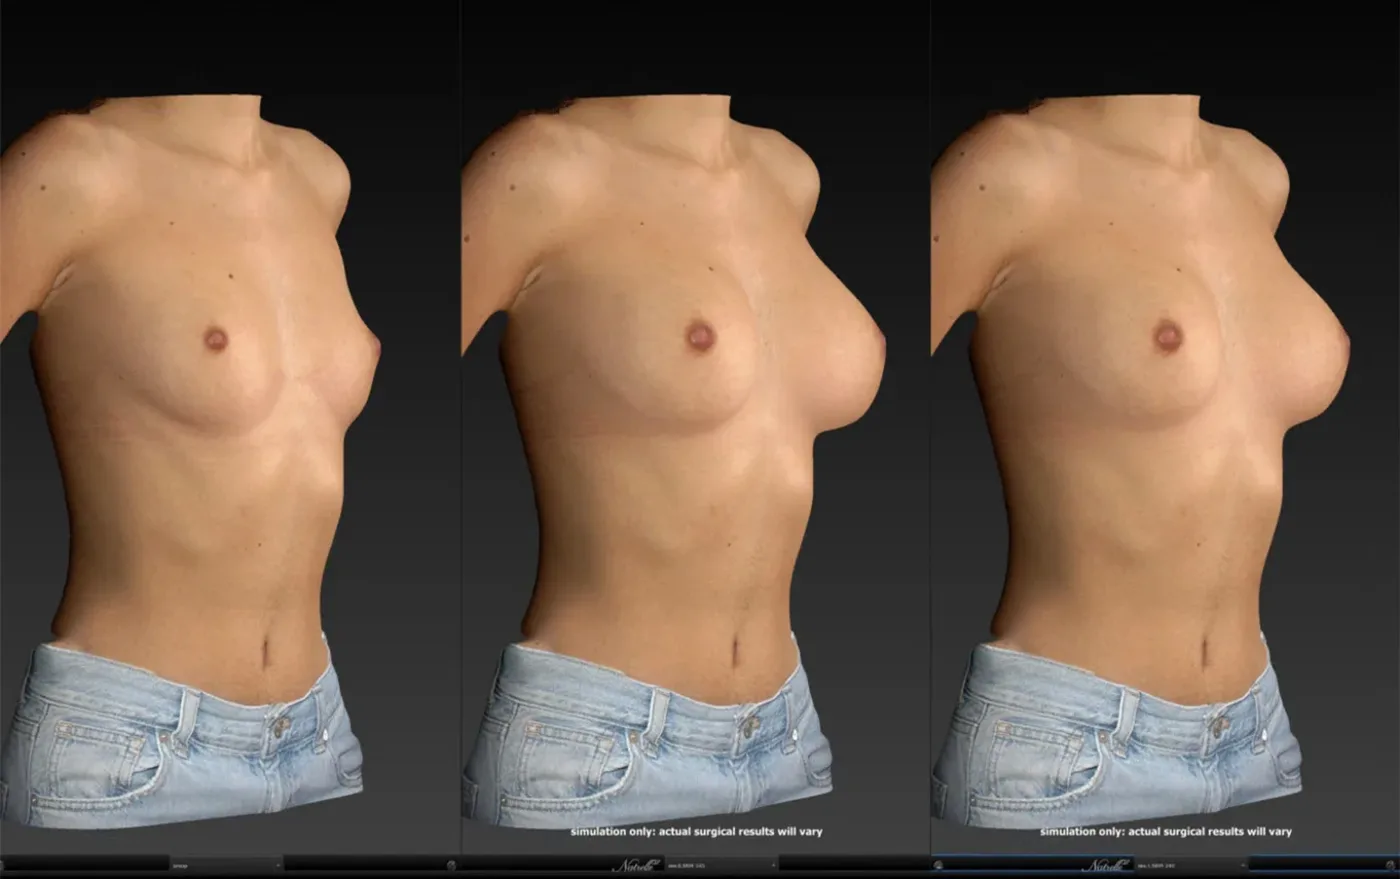
The target is not a specific look — it's the right look for your body, built in four deliberate steps.
Chest wall dimensions, breast base width, tissue quality, and asymmetry are measured first — the implant is chosen to fit them.
When appropriate, dual-plane placement balances implant position against your soft tissue for a natural upper pole and stable coverage.
Keller Funnel insertion within an organized infection-reduction protocol — the implant is never handled directly.
The bra roll, "chicken nuggets," and lateral chest wall are refined in the same operation when your anatomy benefits.
An implant placed into an unframed chest can look bolted on. Dr. Ramirez Gavidia routinely combines liposculpting of the zones around the breast with augmentation — because the borders decide whether the result reads as natural anatomy.

If the breast has descended, adding an implant alone creates a bottom-heavy look — more volume in the wrong place. Patients with both volume loss and ptosis usually need an augmentation-mastopexy: implant plus lift, planned as one structure.

Natural augmentation outcomes are proportional to the frame, soft in transition, and stable over time — enhancement that doesn't announce itself.

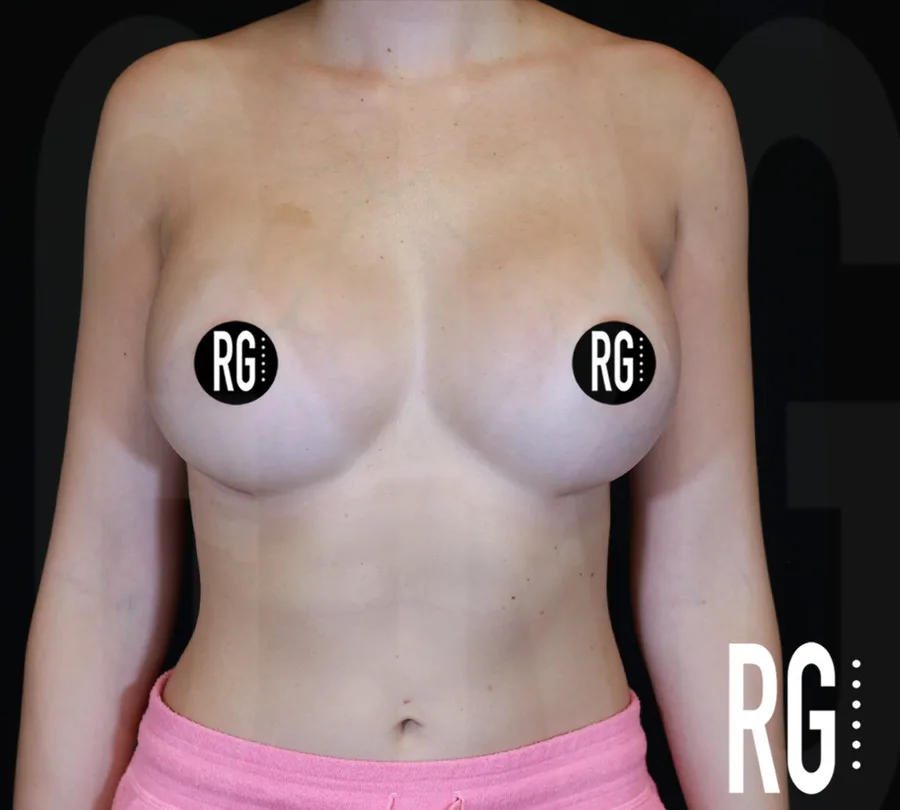
A real RG augmentation, before and after — filmed months after surgery. Nothing staged, nothing retouched.

Implants settle into their final position over two to three months — here's how it typically unfolds.
Up and moving the same day in a surgical support bra. Discomfort managed with oral medication.
Rapid improvement in comfort. Most patients return to desk work.
The majority of swelling resolves. Implants begin to settle into position.
Strenuous upper-body exercise resumes around this point.
Implants drop and soften fully. The final result is visible.
From sizing your implant at consultation to the moment it settles at six months — Dr. Ramirez Gavidia walks the whole progression, including footage from the operating room.

One quote, written at your consultation, built from your plan — implant, pocket, and whether framing liposculpting or a lift is part of it.
You leave your consultation with one written quote for your whole plan.
Breast augmentation is often combined with chest liposculpting — the bra roll and the side of the chest — to frame the result. When it is part of your plan, it is on the same quote, not a surprise later.
Most patients finance part of their surgery. We work with Cherry first — a quick application with no hard credit check to see your options — and we also accept CareCredit.
Neither is universally better. Silicone feels more like natural breast tissue and is the most common choice with adequate coverage; saline allows a smaller incision and intraoperative size adjustment. The right choice depends on your anatomy, coverage, and preferences.
Routinely, yes. Sculpting the bra roll, the anterior axillary fat ("chicken nuggets"), and the lateral chest wall is combined with augmentation whenever it benefits the result — the frame is as important to the final shape as the implant. The exception is very thin patients with little fat around the breast, where framing isn't needed and isn't added.
Implants are not lifetime devices, but they are not replaced on a fixed schedule either. Modern implants are monitored rather than automatically exchanged — replacement is indicated for specific problems, not a calendar date.
Augmentation performed with incisions that avoid the areola and with submuscular or dual-plane placement typically does not affect the ability to breastfeed — though no breast procedure can guarantee it. Discuss this at consultation if it's a consideration.
Yes. Different implant sizes or profiles can be used per side, and significant asymmetry may also benefit from a lift on one or both sides. The achievable correction depends on the nature of the asymmetry.
Breast augmentation at RG Aesthetic Plastic Surgery starts at $8,000. It is often combined with chest liposculpting to frame the result, and both are on one written quote from your consultation. Financing is available through Cherry and CareCredit.
The incision is small and sits in the fold under the breast, toward the side, where it hides well and is covered by a bra or swimsuit. It fades over the first year.
Most augmentations here are dual-plane: the upper part of the implant sits under the muscle for a soft, natural slope, and the lower part sits behind the breast tissue so the breast fills out properly. The pocket is chosen from your tissue coverage, not from a template.
Size starts with measurements — the width of your breast base, your chest wall and your tissue — not a cc number. At your consultation you see implant options on your own body with VECTRA 3D imaging, so the choice is something you can look at, not guess.
Surgery takes about one hour under general anesthesia. Dr. Ramirez Gavidia operates in a hospital surgery center, chosen for maximum sterility.
Most patients are back at desk work in about a week. Lower-body exercise comes back first; strenuous upper-body exercise resumes around four to six weeks.
Dr. Ramirez Gavidia does not combine a tummy tuck with breast surgery in one operation. The abdomen and body contouring are done first, and breast surgery is staged separately — a safer plan with a better result for each area.
If the nipple sits at or below the fold, an implant alone adds volume in the wrong place. In that case a lift with an implant is planned as one structure. Dr. RG shows you where you fall at consultation.
Yes. Consultations are available in English and Spanish at our Franklin office.
Every consultation is with Dr. Ramirez Gavidia himself — a double board-certified plastic surgeon — at our office in Cool Springs.
7105 S Springs Dr, Suite 111
Franklin, TN 37067
615-988-9686
Franklin, Cool Springs, Brentwood, Nashville, Spring Hill, Thompson’s Station, Nolensville, Murfreesboro and across Middle Tennessee.
Implant dimensions, pocket, framing, and proportion are evaluated together at consultation — so the recommendation fits your body, not a template.

